
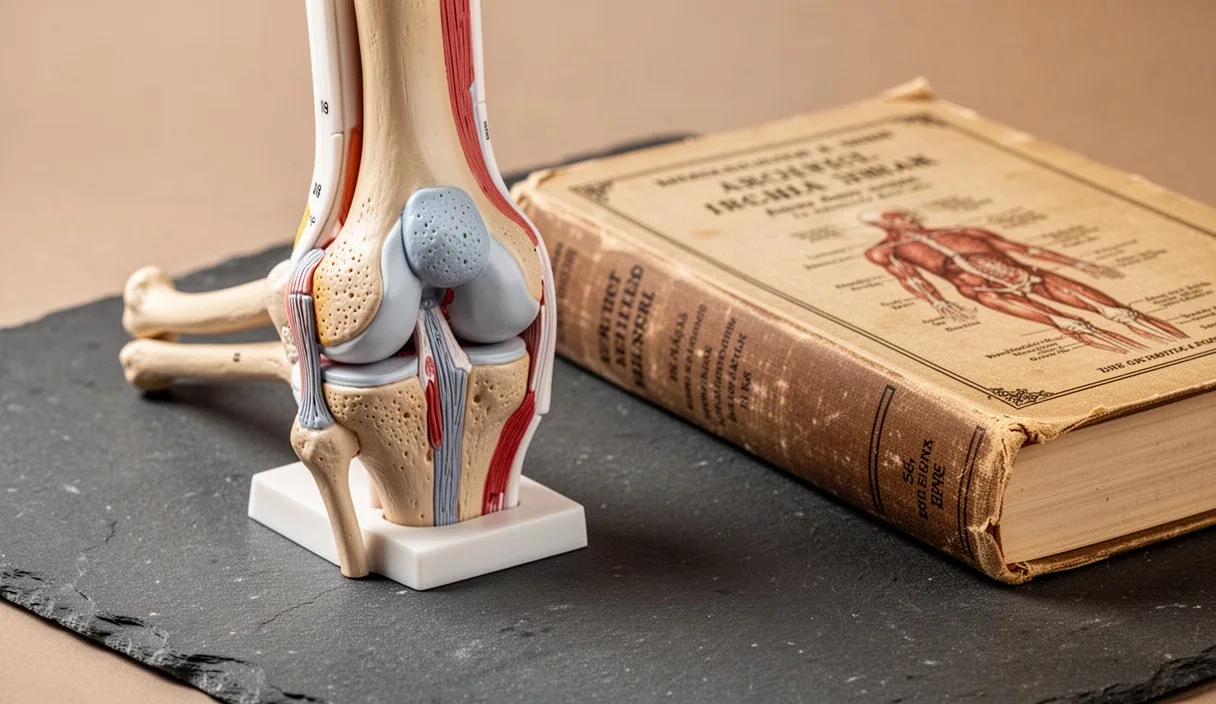

The durability of human articulation depends upon an architectural paradox: the tissue tasked with absorbing the highest repetitive loads in the musculoskeletal system possesses no internal blood supply. Hyaline cartilage, which caps the ends of long bones within synovial joints, operates in metabolic isolation. Lacking capillaries, lymphatic drainage, and nervous innervation, the chondrocytes responsible for maintaining this matrix must survive on nutrient transfer mediated entirely through mechanical work. When an athlete or manual laborer subjects a knee, hip, or ankle to movement, they are not merely performing biomechanical work; they are actively operating an interstitial hydraulic pump.
Synovial fluid is the working fluid of this pump. Produced by the specialized synoviocytes of the inner joint capsule, this ultrafiltrate of blood plasma, enriched with high-molecular-weight hyaluronan and lubricin, bathes the articular surfaces. Under conditions of chronic loading, whether through athletic training, occupational tasks, or corrective rehabilitation, the turnover of this fluid and its transit through the dense network of collagen and proteoglycans determines whether the tissue adapts or degenerates. Understanding these physiological mechanisms strips away much of the mysticism surrounding joint health, replacing speculative interventions with mechanical reality.
The Avascular Nature of Hyaline Cartilage
Adult articular cartilage is predominantly an extracellular matrix populated sparsely by chondrocytes, which occupy roughly one to two percent of the total tissue volume. This matrix is composed of dense water (between 65 and 80 percent of wet weight), a structural mesh of type II collagen fibrils, and large aggregating proteoglycans, notably aggrecan. Because blood vessels cannot penetrate the calcified layer separating cartilage from the subchondral bone without compromising the joint's structural integrity, the metabolic demands of chondrocytes must be met across significant diffusion distances, often spanning two to four millimeters from the articular surface.
This biological isolation imposes strict physiological constraints. Oxygen tensions within the deep zones of hyaline cartilage can drop below two percent, forcing chondrocytes to rely almost exclusively on anaerobic glycolysis for adenosine triphosphate production. Waste products, primarily lactic acid, must exit the tissue along the same tortuous diffusion pathways through which glucose, amino acids, and sulfate ions enter. The density of the surrounding ground substance, charged negatively by the sulfate and carboxylate groups of chondroitin and keratan sulfate chains, exerts a strong electrostatic barrier to the passive movement of solutes.
Consequently, simple passive diffusion is insufficient to sustain matrix homeostasis across the entire depth of the tissue. While low-molecular-weight nutrients like glucose can diffuse slowly into the superficial zone under resting conditions, larger macromolecules and deeper cellular populations depend on the physical displacement of fluid. Without cyclical pressure differentials to propel molecular transport across the pericellular matrix, deeper chondrocytes downregulate their synthesis of aggrecan and link proteins, making tissue maintenance fundamentally contingent on physical movement.
Cyclic Compression as the Engine of Synovial Diffusion
Mechanical loading acts as the primary driver of fluid transport through a process known as weeping lubrication and convective mass transfer. When an axial load strikes the joint surface, the interstitial water within the cartilage matrix is pressurized. Because the proteoglycan gel resists rapid fluid displacement due to low matrix permeability, this fluid pressurization momentarily supports more than 90 percent of the applied load, shielding the delicate collagen scaffold from catastrophic failure.
As the compressive force persists, water is driven slowly out of the matrix into the joint cavity, carrying metabolic byproducts along with it. When the compressive load is removed, the concentrated negative charges on the proteoglycans repel one another, expanding the matrix back toward its original geometry. This elastic recoil drops the internal hydrostatic pressure below that of the synovial cavity, drawing water and freshly dissolved nutrients from the synovial fluid back into the interstitial spaces. In this manner, each stride, pedal stroke, or squat cycle functions as a reciprocating fluid pump.
This cyclic exchange performs two distinct functions:
- Solute convection: The bulk flow of fluid accelerates the transit of larger nutrient molecules through the dense extracellular mesh far beyond the rate achievable by thermal diffusion alone.
- Boundary film renewal: Compressive exudation pushes water and small electrolytes out, leaving behind a concentrated film of lubricin and hyaluronic acid on the articular surface, which preserves low coefficients of friction during high peak loads.
The speed of loading dictates this response. High-frequency impacts do not allow sufficient time for fluid to shift, behaving elastically, whereas excessively prolonged static loads squeeze fluid out entirely, leaving the collagen framework vulnerable to direct mechanical friction. The optimal physiological stimulus falls within cyclic cadences: rhythmic, intermittent deformation followed by immediate unloaded recovery.
Why Immobility Accelerates Articular Matrix Degeneration
When an articulation is immobilized through casting, prolonged bed rest, or sedentary habituation, the hydraulic pumping mechanism ceases. Without cyclical compression, interstitial fluid stagnates. The synovial fluid within the joint space stops circulating freely, leading to a localized accumulation of cellular debris, reduced hyaluronic acid synthesis by type B synoviocytes, and an increase in fluid viscosity that paradoxically impairs boundary-layer lubrication.
Deprived of dynamic fluid turnover, chondrocytes initiate a catabolic cascade. Matrix metalloproteinases (specifically MMP-13) and aggrecanases (ADAMTS-4 and ADAMTS-5) begin cleaving structural proteins faster than the undernourished cells can synthesize replacements. The fixed charge density of the matrix drops as glycosaminoglycan chains degrade, which diminishes the tissue's osmotic swelling pressure. In animal immobilization models, measurable thinning of articular cartilage and reduction in proteoglycan content can be detected in as few as seven to fourteen days of total non-weight-bearing confinement.
Over extended periods, the structural consequences of joint immobility compound:
- Chondrocyte senescence and apoptosis: Cells in the middle and deep zones, starved of glucose and accumulated in unbuffered lactic acid, enter programmed cell death, leaving unmaintained matrix voids.
- Synovial adhesion formation: The synovial membrane folds back upon itself; without motion to preserve the joint recess spaces, fibrofatty connective tissue proliferates, forming intra-articular adhesions that mechanically restrict movement.
- Subchondral bone remodeling: Lacking compressive signals, the underlying subchondral bone undergoes localized osteopenia, while the calcified cartilage zone advances upward, permanently reducing the depth of compliant hyaline tissue.
Shear Stress Versus Axial Compression in Common Movements
Not all mechanical inputs affect hyaline cartilage uniformly. The extracellular matrix is exquisitely adapted to withstand pure axial compression, where hydrostatic pressure distributes the vector across the subchondral surface. It is markedly less capable of handling excessive shear stress, which drags the superficial collagen sheets horizontally across one another, unzipping the fibrillar network and disrupting boundary-layer protection.
The superficial tangential zone of cartilage features collagen bundles aligned parallel to the joint surface to resist tensile loads, but its structural margin of safety is narrow. When movements introduce heavy, unconstrained transverse translation under load, shear forces deform this superficial layer. If shear forces exceed the shear modulus of the tissue, micro-fissuring occurs. These micro-tears allow proteoglycans to leach directly into the joint space, triggering an inflammatory reaction in the synovium and permanently degrading the surface finish.
| Movement Pattern | Primary Force Vector | Synovial Diffusion Dynamic | Matrix Risk Profile |
|---|---|---|---|
| Deep Barbell Squat (Controlled) | High Axial Compression | Robust fluid displacement across broad contact zones | Low shear risk if knee tracking aligns with mechanical foot angle |
| Seated Open-Chain Leg Extension | High Tibiofemoral Shear | Localized patellofemoral compression, minimal fluid exchange elsewhere | Elevated retropatellar shear stress near terminal extension |
| Brisk Walking (Level Surface) | Cyclic Intermittent Compression | High-frequency, low-duration fluid pump ideal for metabolic exchange | Negligible wear; optimal for baseline fluid turnover |
| Aggressive Rotational Cutting | High Multi-Planar Shear | Rapid localized displacement with sudden surface friction | High risk of superficial zone fibril disruption and delamination |
| Stationary Ergometer Cycling | Low-to-Moderate Axial Compression | Continuous low-amplitude hydrodynamic fluid redistribution | Minimal wear; exceptionally low shear profile across arc of motion |
Selecting exercises to encourage tissue nourishment requires evaluating how closely the chosen movement delivers true cyclic compression without excessive, unguided shear. Open-chain resisted extensions create elevated shear forces at specific angles that do not mimic natural load-bearing patterns, whereas closed-chain, multi-joint actions distribute the vector across wider surface areas, dampening regional mechanical stress.
Movement Protocols Designed to Lubricate Restrictive Joints
To restore fluid turnover in joints that have grown stiff or symptomatic from underuse or chronic static loading, programming must prioritize frequency and excursion over load. The primary goal is to circulate synovial fluid across the entire surface area of the articulation, pushing interstitial fluid through regions that remain unloaded during conventional daily routines.
Unloaded Continuous Excursion
This protocol relies on minimal external load to distribute fluid through passive and active reciprocal movement. By cycling a joint through its operational arc without heavy muscular co-contraction, fluid is directed across the outer margins of the condyles without generating destructive shear spikes.
- Mount a stationary bicycle with the seat height adjusted slightly higher than standard to minimize peak knee flexion angles.
- Pedal for 12 to 15 minutes at a steady cadence of 75 to 85 revolutions per minute with zero added flywheel resistance.
- Maintain continuous, uninterrupted pedaling; avoid hard accelerations or sudden coasting periods.
- Perform this routine once daily, ideally upon waking or prior to structured strength training, to lower baseline fluid viscosity.
Controlled Multi-Planar Rotation
Linear movements like walking compress only a discrete, central strip of cartilage. Controlled articular rotations systematically move the joint through its outer borders, ensuring the peripheral cartilage margins, which receive minimal fluid exchange during gait, undergo intermittent pressurization.
- Position the body in a stable quadriped stance on an exercise mat to isolate the targeted hip joint.
- Draw the working knee toward the chest under muscular control, taking three full seconds to reach end-range flexion.
- Abduct the leg laterally while maintaining 90 degrees of knee flexion, avoiding pelvic tilt or lumbar compensation.
- Rotate the femur internally at the peak of abduction, driving the heel upward toward the ceiling over another three-second count.
- Lower the knee smoothly back to the starting point, then immediately reverse the direction of rotation.
- Complete five uninterrupted repetitions per direction on each limb at a slow, deliberate tempo.
Low-Amplitude Oscillatory Pumping
Small, rhythmic compressions within a mid-range joint position stimulate local convective transport without exhausting the stabilizing musculature. This method suits individuals dealing with symptomatic flare-ups where extensive movement arcs provoke discomfort.
- Lie supine and secure a light elastic band around a fixed anchor and the distal ankle of the targeted leg.
- Elevate the leg to roughly 45 degrees of hip flexion with the knee resting in slight, comfortable flexion (roughly 20 to 30 degrees).
- Initiate small, rapid, rhythmic knee extensions and flexions within a narrow arc of 10 to 15 degrees.
- Maintain this flutter-like motion for 45 to 60 seconds at a frequency of approximately two pulses per second.
- Rest for 30 seconds, then repeat for four total rounds per joint.
Common Mistakes in Managing Cartilage Health
One prevalent error is assuming that prolonged rest support joint stiffness. While acute traumatic injuries require temporary stabilization, non-traumatic joint discomfort treated with total inactivity leads to synovial stagnation, accelerated proteoglycan loss, and increased pain upon resuming movement. Rest thickens the fluid and starves the chondrocytes; gradual, unloaded motion is almost always the more constructive physiological choice.
Another error involves loading cold joints with heavy, high-velocity eccentric movements before establishing baseline synovial distribution. Hyaluronic acid displays non-Newtonian shear-thinning characteristics: when resting and cool, it resists flow; under gentle, sustained warmth and motion, its viscosity drops, allowing it to coat the joint evenly. Skipping an unloaded movement preparation period leaves the superficial cartilage zone susceptible to friction-induced mechanical wear during the opening sets of heavy loading.
Finally, individuals frequently conflate range of motion with quality of loading. Forcing an articulation into deep, compromised positions under significant load when mobility restrictions exist introduces destructive horizontal shear vectors. If the hip or ankle lacks adequate dorsiflexion or internal rotation, the knee will twist to compensate, exposing the menisci and retro-patellar cartilage to rotational shear forces that the tissue is structurally unequipped to handle.
Establishing Long-Term Joint Preservation Protocols
Long-term joint cartilage maintenance requires a consistent balance between mechanical stimulation and physiological recovery. Cartilage tissue does not rebuild overnight; chondrocyte turnover of collagen fibrils is measured across years, not weeks. The mechanical objective of training must be to apply enough compressive load to spur nutrient exchange and provoke adaptive proteoglycan synthesis without inflicting mechanical damage on the collagen framework.
Begin by auditing weekly movement habits. Ensure that periods of prolonged sitting or standing are punctuated every 60 to 90 minutes by two minutes of unloaded joint excursions, such as bodyweight leg swings, seated knee extensions, or unloaded ankle circles. For those involved in heavy strength training, program low-load, high-repetition flushing work on off days to sustain fluid turnover without imposing systemic neuromuscular fatigue.
If persistent joint pain, swelling, mechanical catching, or warmth continues despite sensible loading adjustments, seek a comprehensive evaluation from an orthopedic physician or licensed physical therapist. Structural labral tears, advanced chondromalacia, and severe subchondral bone stress warrant targeted diagnostic imaging and clinical oversight. Movement stimulates cartilage biology effectively, but it operates within strict anatomical parameters that must be respected.

